
Paid online consultations are available by appointment. For booking, please contact us via Whatsapp.

In short
What Is Facial Paralysis?
Facial paralysis is the loss of movement in the muscles on one side of the face. It happens when the facial nerve, or the brain area that controls it, stops working. Rarely, it affects both sides.
Specifically, the facial nerve starts in the brainstem and crosses a bony canal behind the ear. It then exits below the ear and fans out into five branches.
The canal is tight, so even mild swelling can block the nerve. Therefore, causes range from viral swelling to a tumor, an injury or a stroke.
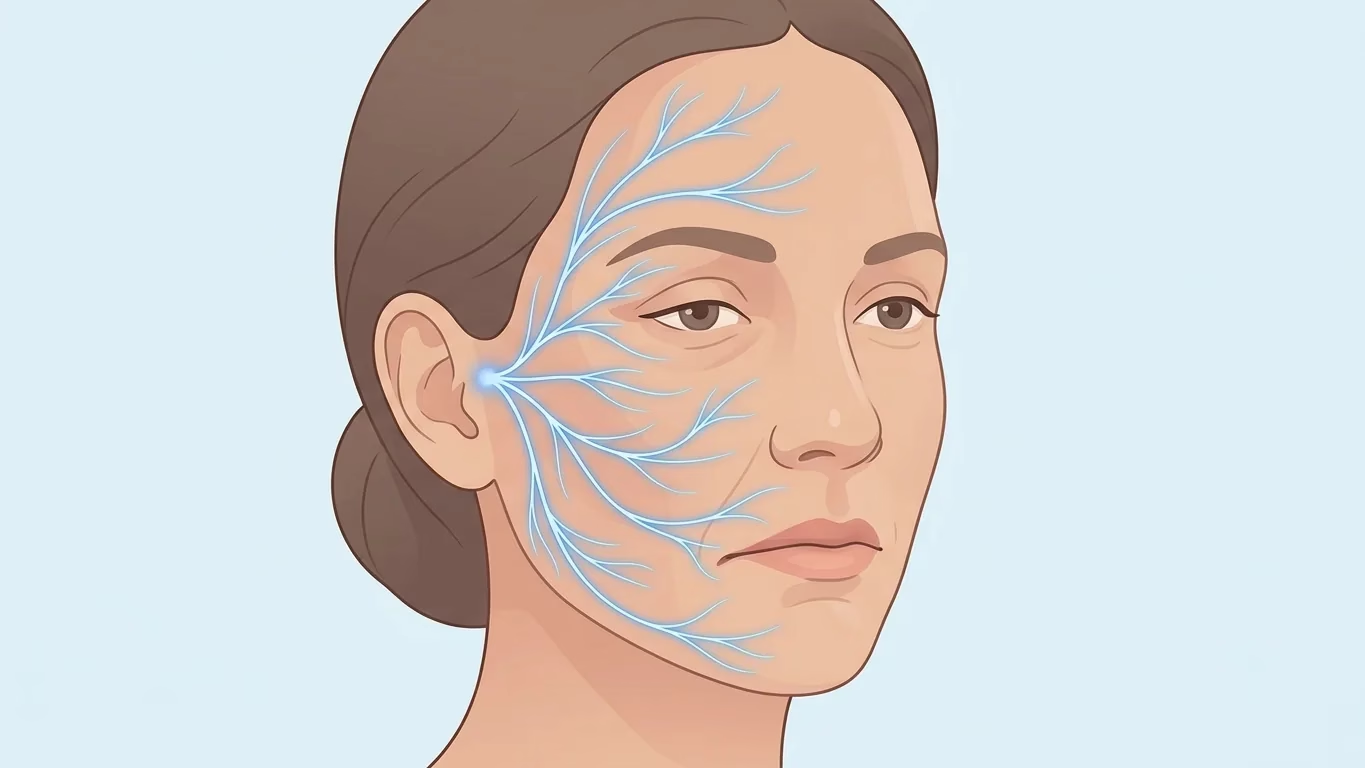
What does the facial nerve control?
In fact, the nerve does more than move the face. As a result, paralysis can affect several functions at once.
- Eye closureBlinking and closing the eye, which protects the cornea
- Forehead and browRaising the eyebrows and wrinkling the forehead
- Smile and mouthSmiling and holding food and drink in the mouth
- Tears and salivaGlands that keep the eye and mouth moist
- TasteTaste from the front two-thirds of the tongue
- Sound controlA tiny ear muscle that softens loud noises
Which Sign Brought You Here?
First, pick the sign that matches what happened. Then, each link explains the likely cause and the next step.
- 01My face drooped over a day or twoOften with pain behind the ear, a taste change or sensitivity to sound
- 02Drooping with arm weakness or slurred speechThe forehead may still wrinkle; this is an emergency
- 03A painful rash in or around the earBlisters, hearing loss or dizziness together with the weakness
- 04Weakness that built up over weeks or monthsTwitching, hearing loss or a lump near the ear
- 05Weakness after a head injury or an operationA skull fracture, a deep facial cut, or ear and skull base surgery
- 06Both sides of the face, or since birthGuillain-Barré syndrome, Lyme disease or a congenital cause
Causes of Facial Paralysis
Facial paralysis has many causes. However, the speed of onset and the signs around it narrow the list quickly.
Bell's palsy
Bell's palsy is the most common cause of facial paralysis. Swelling of the nerve inside its bony canal stops the signals. The weakness then peaks within 48 to 72 hours.
- Pain behind the ear, a change in taste or sensitivity to loud sound
- A drooping brow and mouth, drooling and trouble closing the eye
- Most common between ages 15 and 45; pregnancy, diabetes and high blood pressure raise the risk
Overall, up to 80% of people recover fully within three months. Also, steroids started within 72 hours improve the odds, so early care matters.
Stroke
A stroke damages the brain area that controls the face, not the nerve itself. As a result, the lower face droops while the forehead still wrinkles.
- Sudden onset, often with arm or leg weakness
- Slurred speech, confusion or loss of vision
Call emergency services at once, because stroke treatment works best in the first hours.
Ramsay Hunt syndrome and infections
Ramsay Hunt syndrome is shingles of the facial nerve. It causes a painful rash in or around the ear, often with hearing loss or dizziness.
Recovery tends to be slower than in Bell's palsy, so doctors act quickly. They start antiviral medicine and steroids together. In addition, Lyme disease and middle ear infections can inflame the nerve.
Tumors near the facial nerve
A tumor presses on the nerve slowly, so weakness creeps in over weeks or months. Twitching often comes first. A repeat attack on the same side also calls for an MRI.
- Acoustic neuroma (vestibular schwannoma), usually with hearing loss and imbalance first
- Facial nerve schwannoma and meningioma at the skull base
- Glomus tumors, parotid gland tumors and cholesteatoma of the middle ear
Removing the tumor while protecting the nerve is the neurosurgeon's main task. Read more about skull base tumors and glomus jugulare tumors.
Head injury and surgery
A temporal bone fracture near the ear can bruise or tear the facial nerve. Deep facial cuts and ear or parotid operations can also injure it.
Timing, however, tells the story. Weakness that starts at once suggests a torn nerve, which may need surgery. In contrast, weakness that appears days later usually recovers with medicine.
Both sides, or present from birth
Weakness on both sides is rare and points away from Bell's palsy. Guillain-Barré syndrome, Lyme disease and sarcoidosis, for example, top the list.
Some babies also have facial weakness from birth. It follows a difficult delivery or a rare condition such as Moebius syndrome.
Questions at this stage
Is facial paralysis a stroke?
Not usually. In fact, Bell's palsy causes most cases and weakens the whole side, forehead included. However, a droop with arm weakness or slurred speech needs emergency care at once.
How long does facial paralysis last?
It depends on the cause. For example, Bell's palsy often improves within a few weeks and settles within six months. After nerve damage from a tumor or injury, recovery can take a year or more.
Can stress cause facial paralysis?
Stress alone does not cause it. However, stress, poor sleep and illness can weaken immunity. This may trigger Bell's palsy in some people.
When to See a Doctor
Any new facial weakness needs a same-day medical check. Early treatment works best, and a few causes are also emergencies.
See a doctor the same day if you notice:
- A new droop of the brow, eyelid or mouth corner
- An eye that will not close fully
- Pain behind the ear with a change in taste
- Weakness that keeps worsening after three days
Call emergency services for:
- Face drooping with arm or leg weakness
- Slurred speech, confusion or sudden vision loss
- Facial weakness after a head injury
- A severe headache together with the weakness
Also, return to your doctor if Bell's palsy shows no improvement after three weeks. The same applies, too, if weakness comes back on that side.
Central vs Peripheral Facial Paralysis
In fact, one quick test separates the two main types: wrinkling the forehead.
| Feature | Central (brain) | Peripheral (nerve) |
|---|---|---|
| Where the problem lies | Brain area or pathway that controls the face | Facial nerve, from the brainstem to its branches |
| Forehead | Still wrinkles | Does not move |
| Eye closure | Usually normal | Weak or incomplete |
| Other signs | Arm or leg weakness, speech trouble | Taste change, ear pain, sound sensitivity |
| Typical causes | Stroke, brain tumor, multiple sclerosis | Bell's palsy, Ramsay Hunt syndrome, tumor, injury |
| First step | Emergency stroke care | Same-day exam; steroids for Bell's palsy |
Why does a stroke spare the forehead?
Each side of the forehead receives signals from both halves of the brain. So when one half fails, the other still moves the forehead. A nerve problem, in contrast, cuts off the whole side.
The House-Brackmann Grading Scale
Doctors grade facial nerve function from I (normal) to VI (total paralysis). The grade then guides treatment and tracks recovery.
| Grade | Level | What doctors see |
|---|---|---|
| I | Normal | Normal movement in all areas |
| II | Mild | Slight weakness on close look; the eye closes fully with little effort |
| III | Moderate | Obvious but not disfiguring difference; the eye closes only with effort; some synkinesis |
| IV | Moderately severe | Clear weakness or disfiguring asymmetry; the eye does not close fully |
| V | Severe | Barely visible movement; the face looks uneven even at rest |
| VI | Total paralysis | No movement at all |
Treatment Options for Facial Paralysis
Treatment depends on the cause, the grade and the time since onset. Timing matters most, however, for nerve surgery. Facial muscles fade after about two years without a nerve supply, so delay costs options.
| Option | What it does | Best timing |
|---|---|---|
| Steroids, with antivirals in some cases | Reduce swelling of the nerve | Within 72 hours of onset |
| Eye protection | Drops, ointment, taping or an eyelid weight protect the cornea | From the first day |
| Facial physiotherapy | Retrains control and limits synkinesis | Throughout recovery |
| Botulinum toxin injections | Relax overactive muscles and twitching | Once recovery settles |
| Facial nerve decompression | Opens the bony canal around a swollen or crushed nerve | Early, in selected cases |
| Direct repair or nerve graft | Reconnects a cut nerve; a graft bridges a gap | At once, or within months |
| Nerve transfer | A nearby nerve, such as the hypoglossal or masseteric nerve, powers the face | Within about two years |
| Muscle transfer | A thigh muscle (gracilis) or the temporalis tendon creates a smile | After two years, or when muscles are gone |
| Static procedures | A brow lift, facial sling or eyelid weight improves symmetry at rest | Any time |
When Facial Paralysis Needs a Neurosurgeon
A neurosurgeon steps in when the cause lies inside the skull. Moreover, the nerve's path there runs right beside the hearing and balance nerves.
During skull base surgery, for example, nerve monitoring helps the surgeon protect the facial nerve. If a tumor destroys part of the nerve, the surgeon then repairs it at once. A graft can also bridge a longer gap.
Hypoglossal-facial nerve anastomosis helps when the nerve end near the brainstem is lost. Here, the surgeon links part of the tongue nerve to the facial nerve. Movement then returns gradually over months.
Neurosurgeons also treat brainstem lesions, such as cavernomas, that can weaken the face. In addition, facial pain without weakness points to another nerve; see facial nerve pain.
Your treatment path
From Diagnosis to Recovery
Care follows four steps, from the first exam to the return of movement. However, not every patient needs all four.
STEP 01
Diagnosis: finding the cause
First, the exam checks which parts of the face move, starting with the forehead. The doctor then records the grade. Hearing, the ears and the other cranial nerves come next.
- MRI with contrast shows tumors, stroke or inflammation along the nerve.
- CT of the temporal bone shows fractures and middle ear disease.
- Electroneurography (ENoG) and EMG, between days 3 and 14, estimate how many nerve fibers still work.
- Blood tests look for Lyme disease or diabetes when relevant.
When do doctors order an MRI for facial paralysis?
Doctors generally order an MRI when weakness builds slowly, worsens or returns on the same side. They also order one when other nerve signs appear or recovery stalls for three months.
STEP 02
Early care: the first 72 hours
For Bell's palsy, steroid tablets started within 72 hours improve recovery. In severe cases and in Ramsay Hunt syndrome, doctors also add antiviral medicine.
Next, eye care starts on day one: drops by day, ointment and taping at night. Meanwhile, a stroke needs emergency care, and infections need their own treatment.
Can facial paralysis be cured?
Often, yes. In Bell's palsy, for example, up to 80% recover fully within three months. However, paralysis from a cut or long-damaged nerve needs surgery to restore movement.
STEP 03
Surgery: restoring the nerve or the smile
Surgery follows the clock. Early on, for instance, a surgeon can release a crushed nerve or repair a cut one.
- Up to about two years: a nerve graft or a nerve transfer, such as hypoglossal-facial anastomosis, brings new signals to the face.
- After about two years: a muscle transfer, such as a gracilis flap from the thigh, creates a new smile.
- At any stage: an eyelid weight, brow lift or facial sling improves comfort and symmetry.
Nerve surgery generally takes place under general anesthesia. After a muscle transfer, patients typically stay in hospital for two to three days.
STEP 04
Recovery: retraining the face
Nerves regrow slowly. After a nerve transfer, the first movement often appears in four to six months. Facial physiotherapy then trains the new connections into a controlled smile.
Some patients develop synkinesis, such as the eye closing during a smile. Botulinum toxin and targeted exercises, however, ease it well.
When can international patients fly home?
Your surgeon decides this at the post-operative check. In general, patients fly once the wound heals well. A local physiotherapist then continues the exercises.
Facial Nerve Surgery in Istanbul

Prof. Dr. Serdar Baki Albayrak
Neurosurgeon · Skull Base and Nerve Surgery
Facial paralysis surgery depends on timing, because nerve options close as the muscles weaken. Therefore, Prof. Albayrak plans each case around the cause, grade and time since onset.
27+Years
5,000+Operations
64Countries
Figures from Prof. Albayrak's professional profile, September 2026.
Request an AppointmentFrequently Asked Questions
What is the difference between Bell's palsy and facial paralysis?
Facial paralysis describes the weakness itself. Bell's palsy, however, is one cause, and doctors name it only after ruling out others.
Is facial paralysis permanent?
Most cases improve, especially Bell's palsy. Lasting weakness is more likely after a complete palsy, Ramsay Hunt or a cut nerve. Even then, surgery can restore tone and a smile.
Can facial paralysis come back?
Bell's palsy returns in about 5 to 10% of people. A repeat attack on the same side, however, needs an MRI.
Which doctor treats facial paralysis?
A neurologist or ENT specialist usually starts care. Neurosurgeons then treat tumors, brainstem lesions and nerve repairs. Prof. Dr. Serdar Baki Albayrak treats these causes in Istanbul.
Prof. Albayrak's Published Research
Peer-reviewed articles and book chapters written or co-written by Prof. Dr. Serdar Baki Albayrak on nerve injury and nerve repair. Each link opens the record on PubMed or at the publisher. The full list of his 33 publications is on his profile.
- Doxorubicin for prevention of epineurial fibrosis in a rat sciatic nerve model: outcome based on gross postsurgical, histopathological, and ultrastructural findings
- Topical Application of Cyclosporine Reduces Epineurial Fibrosis: Gross Postsurgical, Histopathological and Ultrastructural Analysis in a Rat Sciatic Nerve Model
- Management outcome of peroneal nerve injury at knee level: experience of a single military institution
Public health information
- National Institute of Neurological Disorders and Stroke. Bell's Palsy.
- NHS. Bell's palsy.
- National Institute on Deafness and Other Communication Disorders. Vestibular Schwannoma (Acoustic Neuroma) and Neurofibromatosis.
This page gives general medical information and does not replace a consultation. Diagnosis and treatment decisions need an examination by your own doctor.
Plan Your Facial Nerve Care in Istanbul
Request an appointment with Prof. Dr. Serdar Baki Albayrak. The clinical team then guides international patients through every step of the visit.
Request an Appointment